
 Pay Bill


Quick Links


2027 Benefits at a Glance
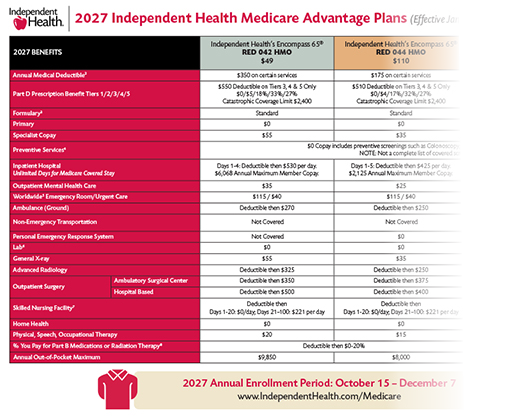
Review Independent Health’s 2027 Medicare Advantage Plans with our 2027 Benefits at a Glance tool. Learn More
Independent Health's
2027 Encompass 65® Red 042 HMO
MONTHLY PREMIUM
PRIMARY/SPECIALTY COPAY (In-Network)
INPATIENT HOSPITAL COPAY (In-Network)
PART D PRESCRIPTION BENEFIT
(Tier 1 / 2 / 3 / 4 / 5)
MONTHLY PREMIUM
$49
PRIMARY/SPECIALTY COPAY (In-Network)
$0/$55
INPATIENT HOSPITAL COPAY (In-Network)
$350 deductible then $530 per day for days 1 through 4. $0 copay for days 5 through 90. Unlimited days. $6,068 copay maximum.
PART D PRESCRIPTION BENEFIT
$550 deductible on tiers 3, 4 & 5 only. $0/$5/18%/33%/27% to Catastrophic Coverage Limit of $2,400.
Independent Health's
2027 Encompass 65® Red 044 HMO
MONTHLY PREMIUM
PRIMARY/SPECIALTY COPAY (In-Network)
INPATIENT HOSPITAL COPAY (In-Network)
PART D PRESCRIPTION BENEFIT
(Tier 1 / 2 / 3 / 4 / 5)
MONTHLY PREMIUM
$110
PRIMARY/SPECIALTY COPAY (In-Network)
$0/$35
INPATIENT HOSPITAL COPAY (In-Network)
$175 deductible then $425 per day for days 1 through 5. $0 copay for days 6 through 90. Unlimited days. $2,125 copay maximum.
PART D PRESCRIPTION BENEFIT
$510 deductible on tiers 3, 4 & 5 only. $0/$4/17%/32%/27% to Catastrophic Coverage Limit of $2,400.
Independent Health's
2027 Encompass 65® Red 045 HMO
MONTHLY PREMIUM
PRIMARY/SPECIALTY COPAY (In-Network)
INPATIENT HOSPITAL COPAY (In-Network)
PART D PRESCRIPTION BENEFIT
(Tier 1 / 2 / 3 / 4 / 5)
MONTHLY PREMIUM
$286
PRIMARY/SPECIALTY COPAY (In-Network)
$0/$25
INPATIENT HOSPITAL COPAY (In-Network)
$300 copay per day for days 1 through 6. $0 copay days 7 through 90. Unlimited days. $1,800 annual copay maximum.
PART D PRESCRIPTION BENEFIT
$375 deductible on tiers 3, 4 & 5 only. $0/$4/16%/42%/29% to Catastrophic Coverage Limit of $2,400.
Independent Health's
2027 Encompass 65® HMO (without prescription coverage)
MONTHLY PREMIUM
PRIMARY/SPECIALTY COPAY (In-Network)
INPATIENT HOSPITAL COPAY (In-Network)
PART D PRESCRIPTION BENEFIT
(Tier 1 / 2 / 3 / 4 / 5)
MONTHLY PREMIUM
$0
(Independent Health pays $60 per month toward your Part B premium)
PRIMARY/SPECIALTY COPAY (In-Network)
$0/$30
INPATIENT HOSPITAL COPAY (In-Network)
Days 1-5: $300 per day. Additional days: $0. Unlimited Days for Medicare covered stays. ($1,500 Annual Member Copay Maximum).
PART D PRESCRIPTION BENEFIT
No Part D prescription drug benefit.
Independent Health's
2027 Medicare Passport® Connect PPO
MONTHLY PREMIUM
PRIMARY/SPECIALTY COPAY (In-Network)
INPATIENT HOSPITAL COPAY (In-Network)
PART D PRESCRIPTION BENEFIT
(Tier 1 / 2 / 3 / 4 / 5)
MONTHLY PREMIUM
$81
PRIMARY/SPECIALTY COPAY (In-Network)
$0/$55
INPATIENT HOSPITAL COPAY (In-Network)
Days 1-5: $450 per day (IN). Days 7-90: $0 (IN). Unlimited Days for Medicare covered stays (IN). ($2,250 Annual Member Copay Maximum) (IN).
PART D PRESCRIPTION BENEFIT
In-Network and Out-Of-Network. $700 deductible on all tiers. 25%/25%/25%/25%/25% to Catastrophic Coverage Limit of $2,400.
Independent Health's
2027 Assure Advantage® HMO C-SNP Plan
This is a chronic special needs plan (C-SNP), specifically developed for eligible Medicare beneficiaries who have been diagnosed with chronic heart failure and reside in Erie County.
Independent Health's
2027 Medicare Family Choice® HMO I-SNP Plan
This plan is specifically designed to help you stay involved with the care of your loved one living in a nursing home or an assisted living facility with the help of a coordinated care team.
Interested in our plans?
We are here to help! You can request a copy of our full sales kit to help explain the differences between each plan.
Notice of Availability of Language Assistance Services and Nondiscrimination Notice
Disclaimers
Every year, Medicare evaluates plans based on a 5-star rating system. Out-of-network/non-contracted providers are under no obligation to treat Independent Health members, except in emergency situations. Please call our customer service number or see your Evidence of Coverage for more information, including the cost sharing that applies to out-of-network services.
IN = In-Network, OON = Out-of-Network
Y0042_C7173
Last Updated 10/1/2026